Cerebral Blood Flow and Intracranial Pressure
Take home messages
- Understanding the factors that influence intracranial pressure is crucial to safely managing patients with head trauma
- In district general hospitals where intracranial pressure monitoring isn't available, you may have to 'assume' a raised pressure to be on the safe side
Podcast episode
A spot of history
A long, long time ago, before anaesthesia and CT scans - or medicine really - if you behaved strangely it was 100% because there was a demon in your head and the best way to release it was obviously with a drill to the skull.
Preferably while wearing an upside down funnel, and with your ODP balancing the controlled drugs book on their head.


This procedure dates back as far as 10,000 years ago, and amazingly, the mortality rate (for an unsterile, unguided drill to the skull, while outside in a field) is believed to only have been around 60%.
While the techniques and indications have evolved and improved somewhat since then, the underlying principle for a lot of intracranial pathology is the same:
Enter the Monro-Kellie doctrine
The skull is a fixed container of around 1700ml volume, with a lot of little holes, and one big one at the bottom.
Inside said fixed box of bone there exist three types of content:
- Brain 80%
- Blood 10%
- CSF 10%
These three live in a constant harmonious balance wherein if any one of them increases in volume, in order to avoid a harmful rise in intracranial pressure, one or both of the others must graciously decrease in volume to compensate.
Otherwise you get this graph:
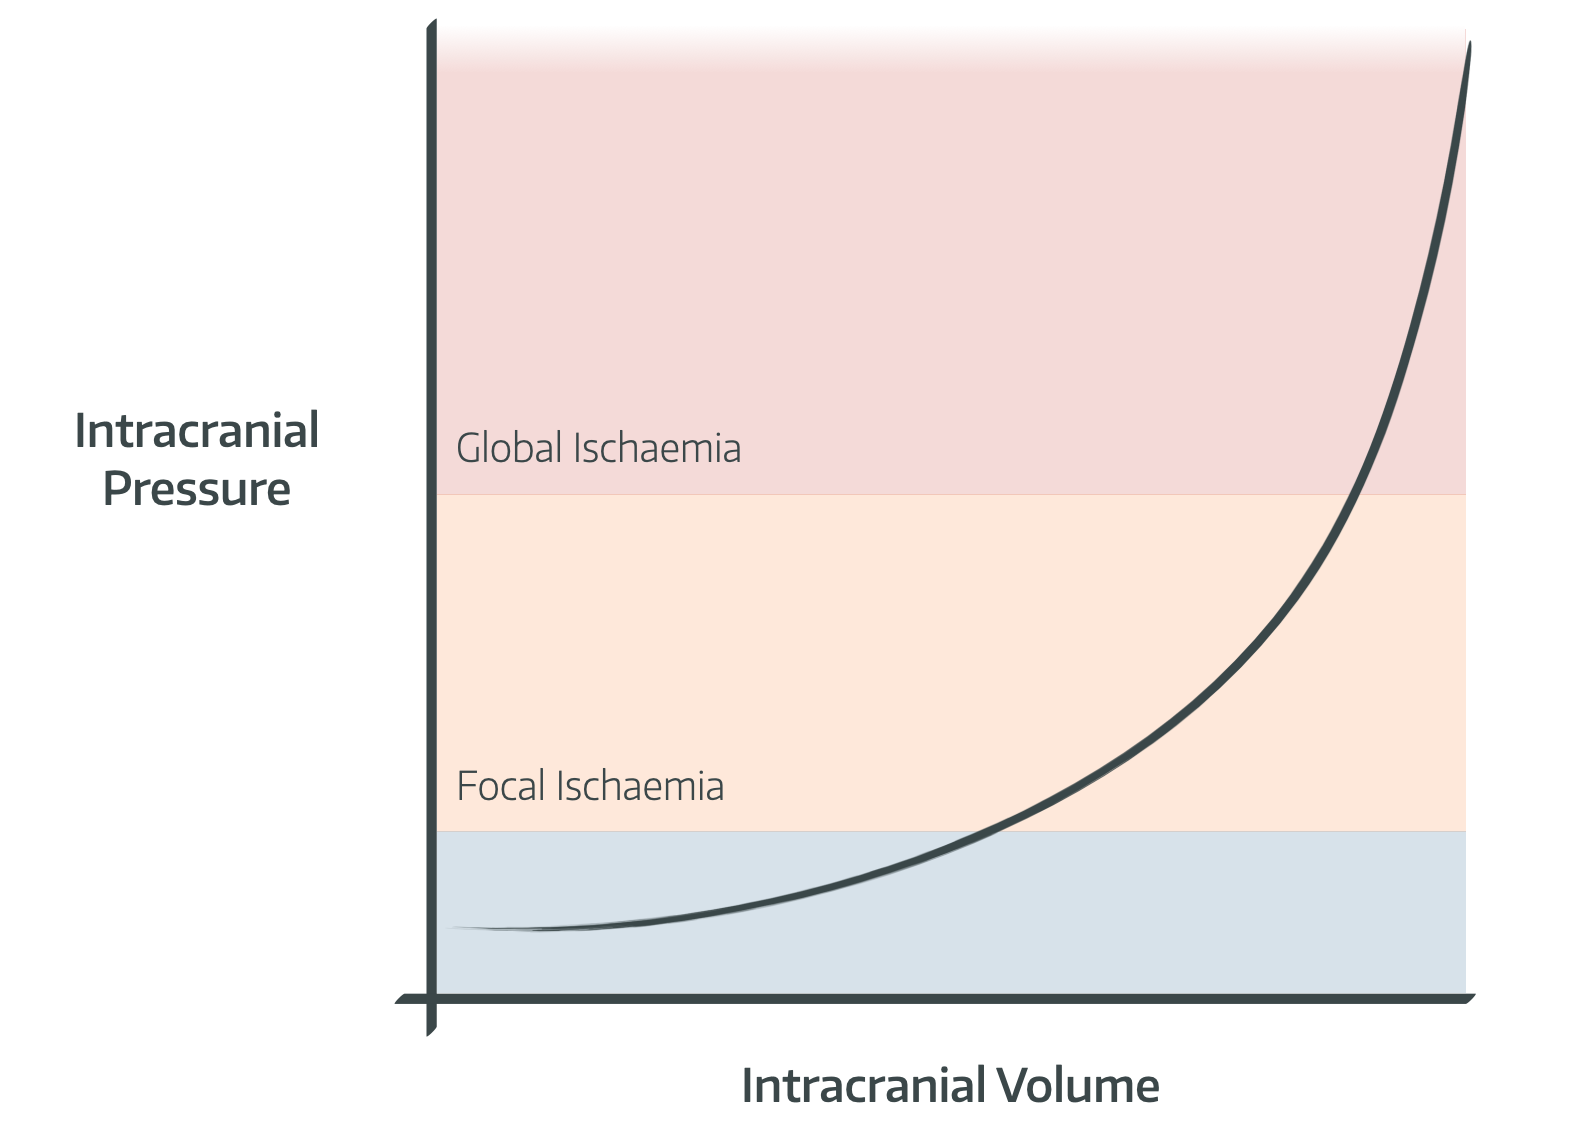
- Note that normal intracranial pressure, when lying supine, is approximately 8-12 mmHg
- Above 20 mmHg there starts to be focal ischaemia
- Above 45-50 mmHg there is global ischaemia
Which brings us nicely to a classic FRCA question.
What are the causes of raised intracranial pressure?
This is a very common exam question, and prime CASE/FCPE fodder.
The key to a strong answer is, as always, to categorise.
Increased CSF in the brain:
- Overproduction
- Underabsorption
- Blockage of drainage
All three of these can lead to hydrocephalus.
Mass effect of the brain itself:
- Oedema
- Contusion
- Abscess
- Tumour
Increased intracranial blood volume:
- Venous obstruction
- Venous sinus thrombosis
- Haemorrhage
Benign intracranial hypertension is a strange neurological phenomenon associated with increased CSF pressure of unclear aetiology. It is associated with obesity and it is also far from benign.
What happens when intracranial pressure starts to increase?
There are three main compensatory mechanisms in place to deal with increasing intracranial pressure to try and prevent neurological catastrophe.
- Initially venous blood is pushed out of the skull, reducing the volume of blood in the great veins and sinuses
This is why it's a good idea to avoid jugular central lines, and anything else that might obstruct venous drainage such as tube ties (use tape instead).
It's also why we nurse the patient head up around 30°, to let gravity assist venous drainage.
- Secondly, cerebrospinal fluid is extruded via the foramen magnum
There's a total volume of approximately 150ml of CSF, with around 125ml of this in the subarachnoid space (both brain and spinal cord), and only about 25ml in the ventricles.
This might not seem like much, but if you consider the steep gradient of the curve in the graph above, you only need a small reduction in volume to substantially reduce the pressure.
- Thirdly the volume of arterial blood starts to reduce
This is a bad thing, and it's why increasing pressure causes ischaemia. The arterial supply is no longer able to push through the brain tissue to supply it with oxygen, and everything starts to shut down.
After a certain point, there won't be anything else that can be removed to accomodate the expanding volume, and only very small increases in volume will dramatically increase intracranial pressure, causing physical compression of the brain parenchyma and ischaemia.
This may eventually lead to herniation and death.
What are the clinical features of raised intracranial pressure?
These can be gradual, insidious and non-specific, requiring a relatively high level of suspicion if you're going to spot the diagnosis.
- Headache, worse on straining or bending over
- Nausea and vomiting
- Papilloedema
- Reduced GCS or irritability
- Bulging fontanelle in infants
Of course there can be other, more obvious signs pointing to the possibility of rising intracranial pressure, such as a mangled Ford fiesta with a bullseyed windshield.
The Cushing Reflex is a preterminal sign
The Cushing Reflex is a last ditch survival mechanism used by the failing brain to maintain its own oxygenation.
- Raised intracranial pressure leads to hypoperfusion
- The brain releases vasoactive mediators to increase blood pressure and restore blood supply
- This increased blood pressure causes a reflex bradycardia, and further increases intracranial pressure
- The increasing pressure leads to herniation of brainstem through foramen magnum, stretching the cranial nerves
- This is known as coning
Hypotension, apnoea and fixed dilated pupils follow once cushing’s reflex fails.
Talk to me about cerebral blood flow
As one might expect, the brain receives rather a lot of blood in order to sustain all of those thoughts and decisions, and ends up receiving around 25% of the cardiac output.
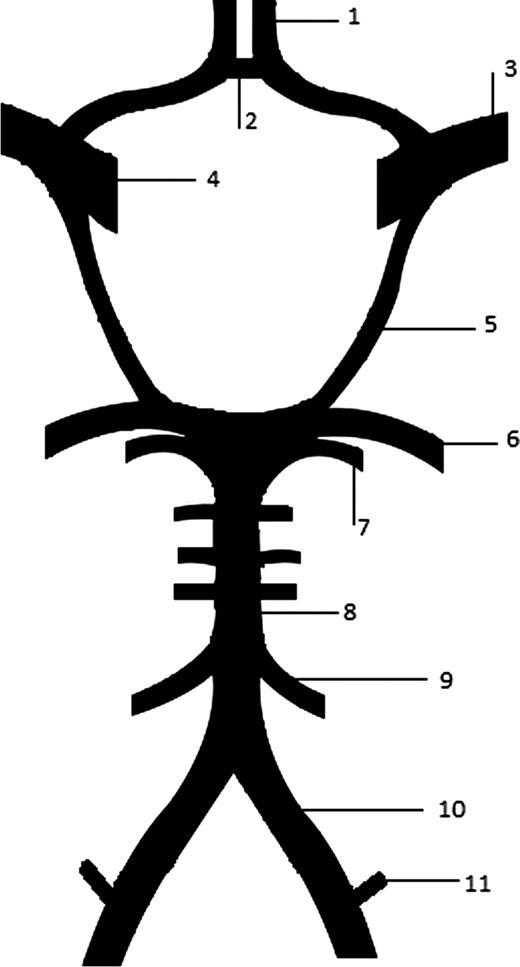
Now it seems risky plumbing such an important organ into one or two individual arteries that then have to traverse the tiger country that is the neck, so a clever anastomosis has evolved to introduce some redundancy and resilience into the brain's blood supply.
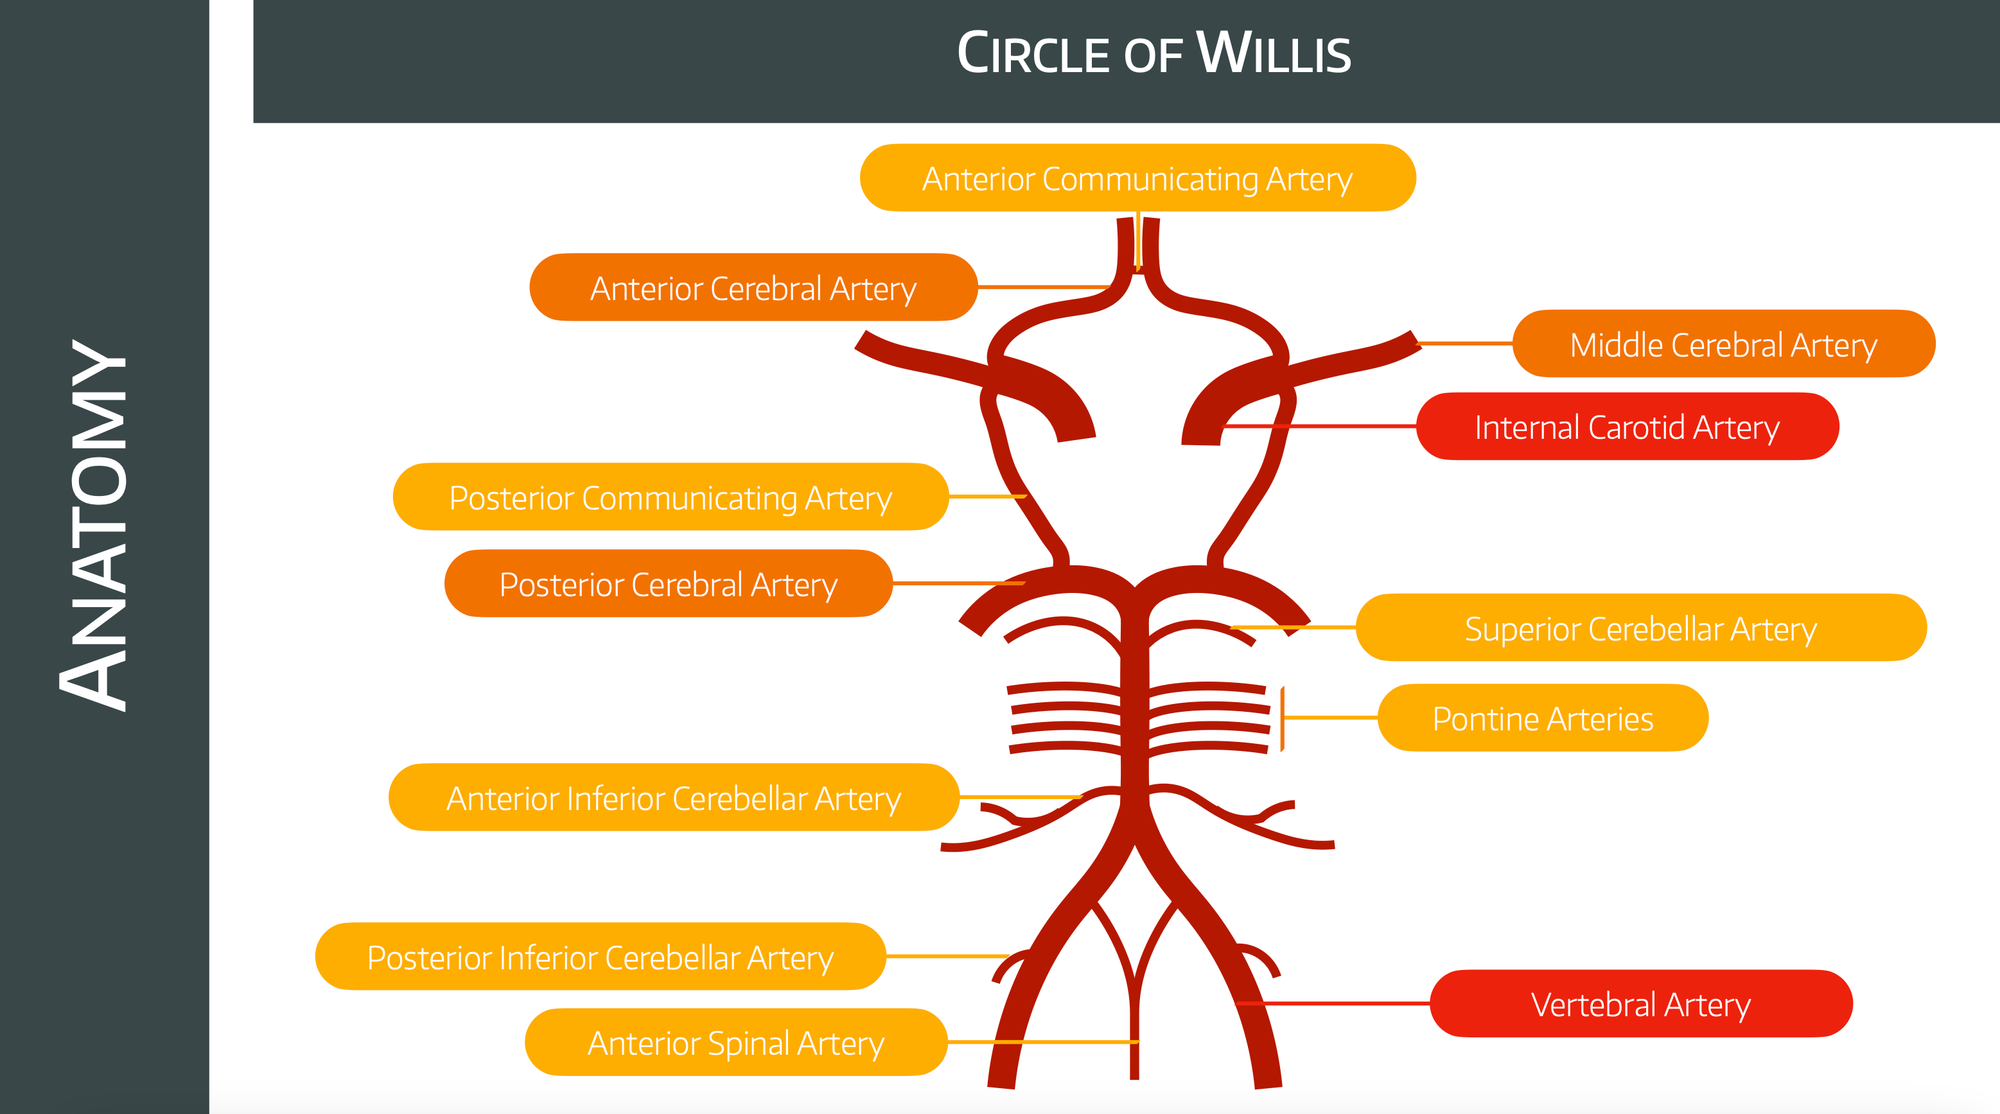
The key points in this diagram are as follows:
- 75% (ish) of blood supply to the brain is via the internal carotid arteries
- 25% (ish) is via the vertebral arteries
- The circle of Willis is a beautiful anastomosis that connects all four arteries
- This means theoretically that up to three of these arteries can become compromised or blocked and the brain will still be adequately perfused
How this fares in reality is a different matter, but it's a neat solution to the problem nonetheless.
What factors influence cerebral blood flow?
Aha, a massive question with equally massive potential to score you loads of marks on exam day.
It's also quite important to understand this stuff, you know, to look after patients and whatnot.
To answer this question, start with the mic-drop opener of:
"Factors influencing cerebral blood flow relate to the Hagen Poiseuille equation, as follows:"
Q = πΔPr4/8ɳl
Where:
- Q = Flow
- ΔP - change in pressure
- ɳ - viscosity
- l - length of tube
When you inject local anaesthetic through a peripheral nerve block catheter, you have to push really hard to get any flow, because the tube is very long with a tiny radius.
A grey cannula, on the other hand, is ideal for resuscitation as it is short and wide.
When it comes to cerebral blood flow, the two variables that matter are the pressure gradient and blood vessel radius.
Pressure gradient
The key term to talk about is cerebral perfusion pressure.
Cerebral Perfusion Pressure = Mean Arterial Pressure – (ICP + CVP)
- Where ICP = intracranial pressure and CVP = central venous pressure
This is the blood pressure that the brain is actually feeling, and it means that raised intracranial pressure will need a larger mean arterial pressure in order to adequately perfuse the brain.
If you have a patient with suspected raised ICP, assume it is around 20 mmHg and aim for a MAP of at least 90 mmHg.
Blood vessel radius
The main factors that induce vasoconstriction and dilation are:
- PaCO2
- PaO2
- Metabolic waste products such as H+, K+ and adenosine
If there's not enough oxygen, the vessels dilate to increase flow.
If there's too much CO2 or waste buildup, the same happens.
How does PaCO2 influence cerebral blood flow?
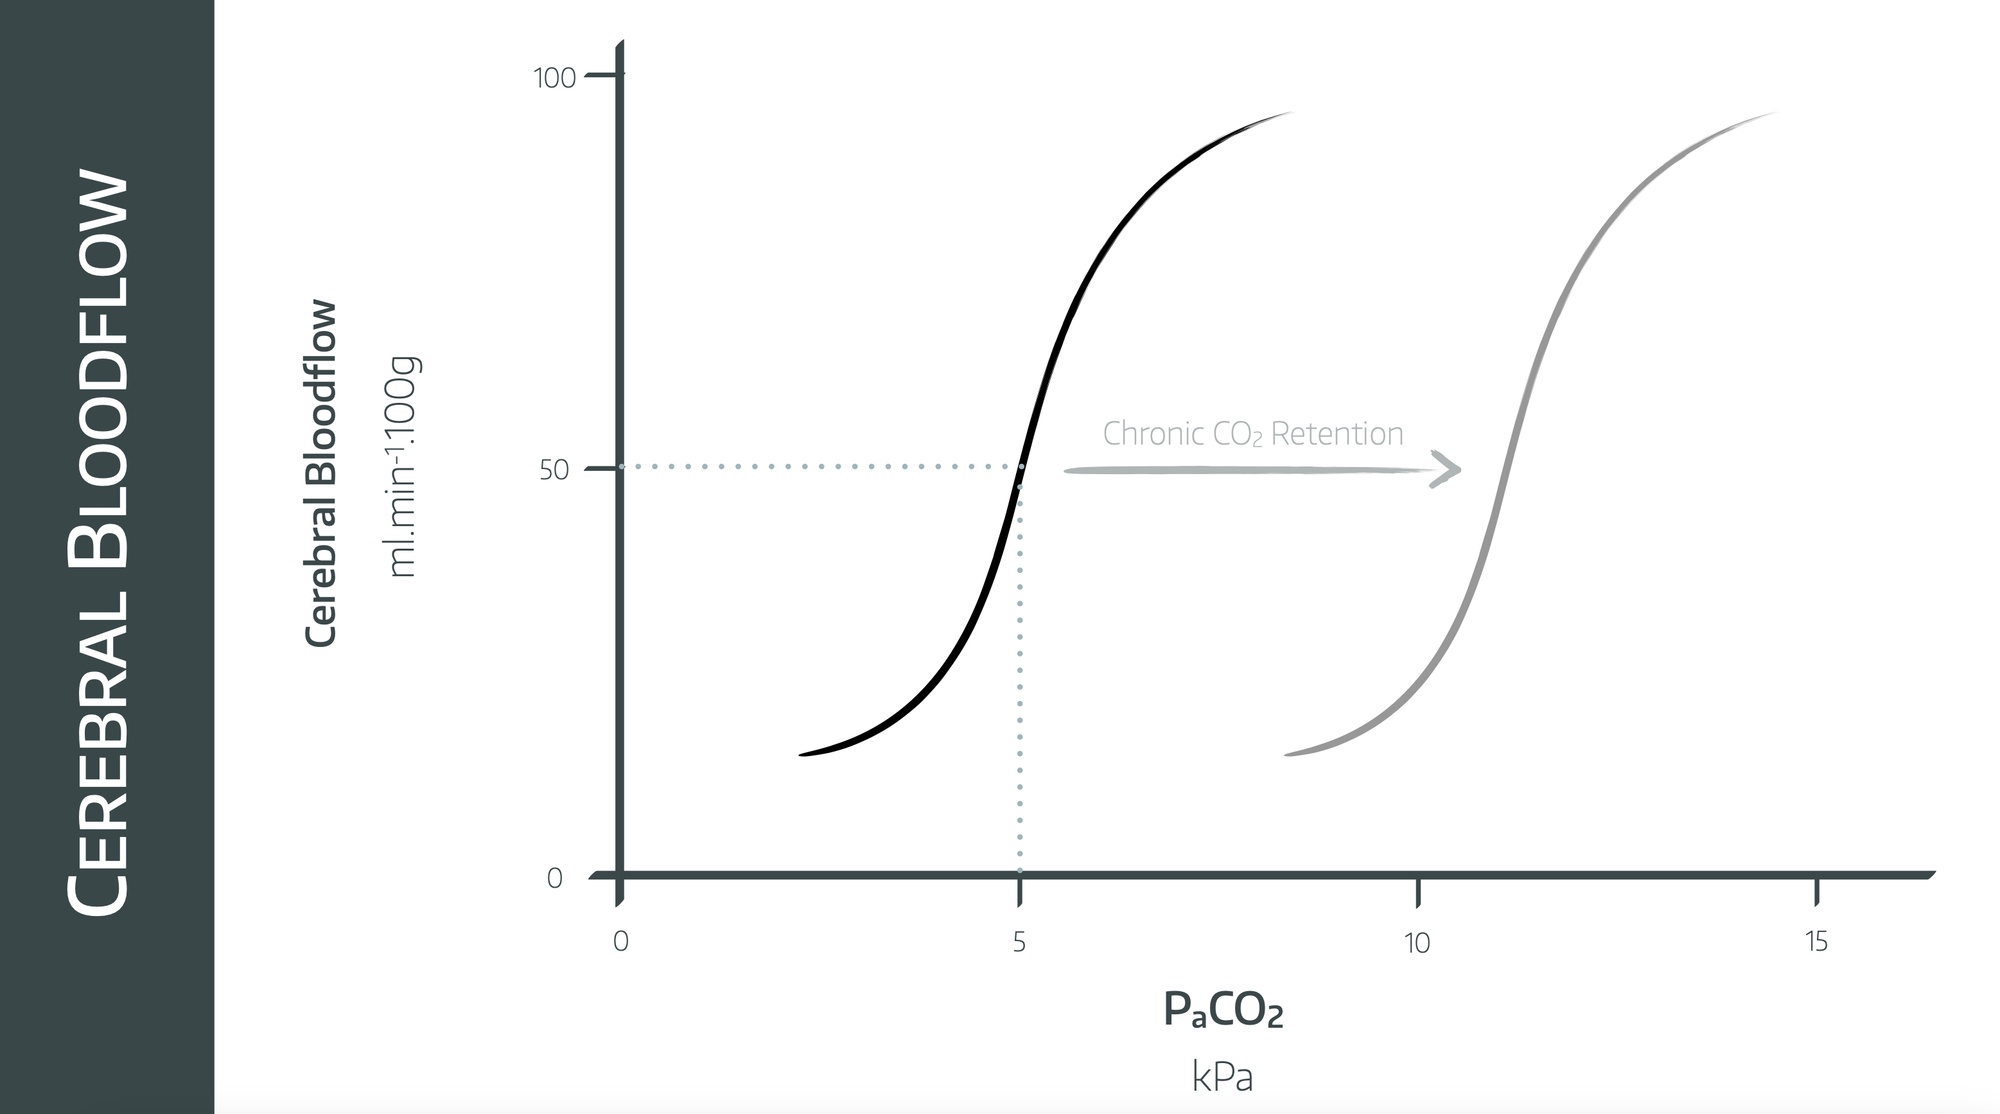
Cerebral blood flow increases with PaCO2 as a result of vasodilatation, and this is essentially linear over the physiologically encountered ranges between 4 kPa and 8 kPa.
The sigmoid graph plateaus at either end as the ability of the blood vessels to constrict or dilated is maxed out.
In chronic hypercapnoea the graph is shifted to the right as a result of compensatory buffering. Bicarbonate is actively pumped into the CSF to buffer the increased hydrogen ion concentration caused by chronic hypercapnoea.
How does PaO2 affect cerebral blood flow?
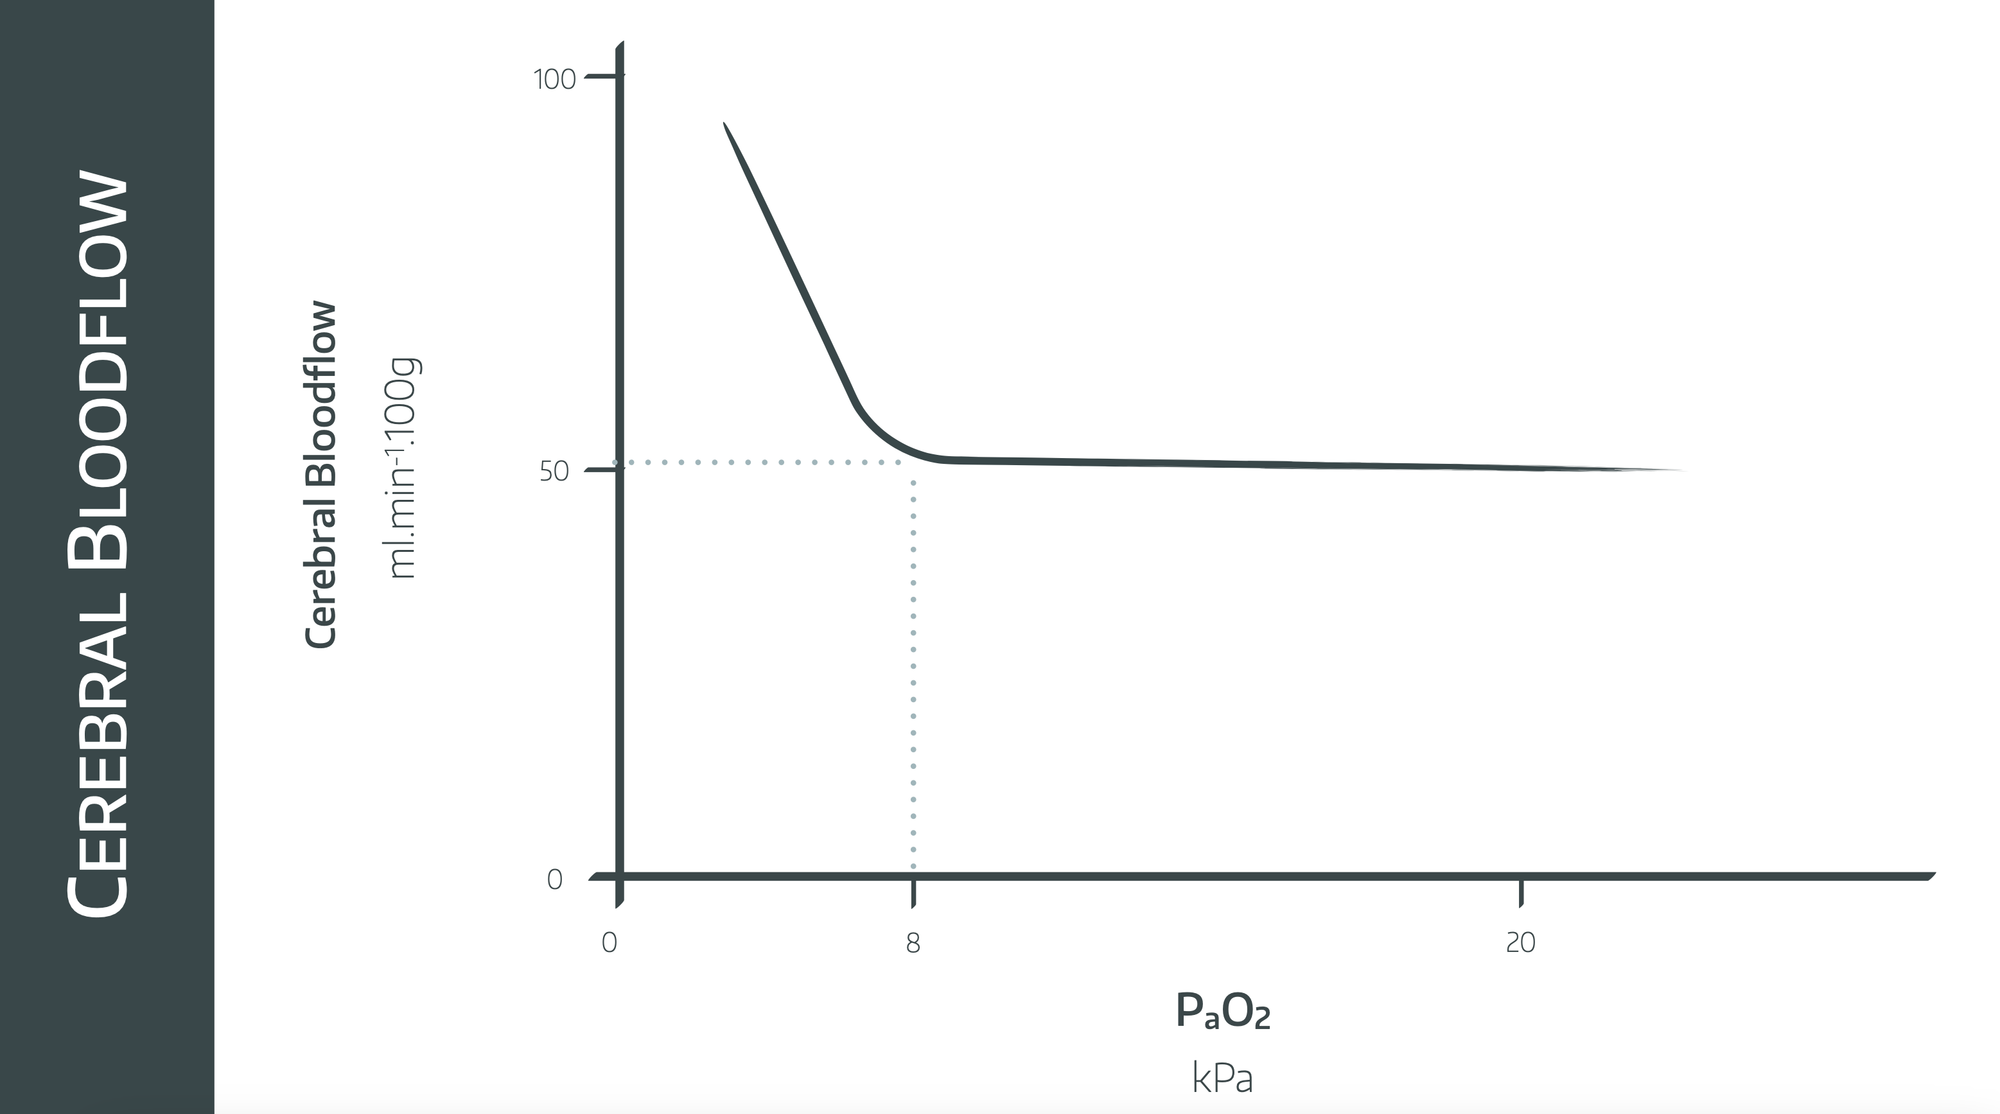
Cerebral blood flow is fairly stable above a PaO2 of 8 kPa. Below this, vasodilatation causes a rapid increase in cerebral blood flow.
This response is very strong and will overpower any vasoconstriction caused by other mechanisms.
What is flow-metabolism coupling?
The rate at which the brain consumes oxygen through metabolism is the cerebral metabolic rate or oxygen utilisation or CMRO2
- Usually around 3ml/100g/minute
- 5ml/100g/minute in young children
Flow-metabolism coupling is where perfusion is adjusted to match the metabolic demand of a given region of the brain, or the brain as a whole.
More demand = more blood supply.
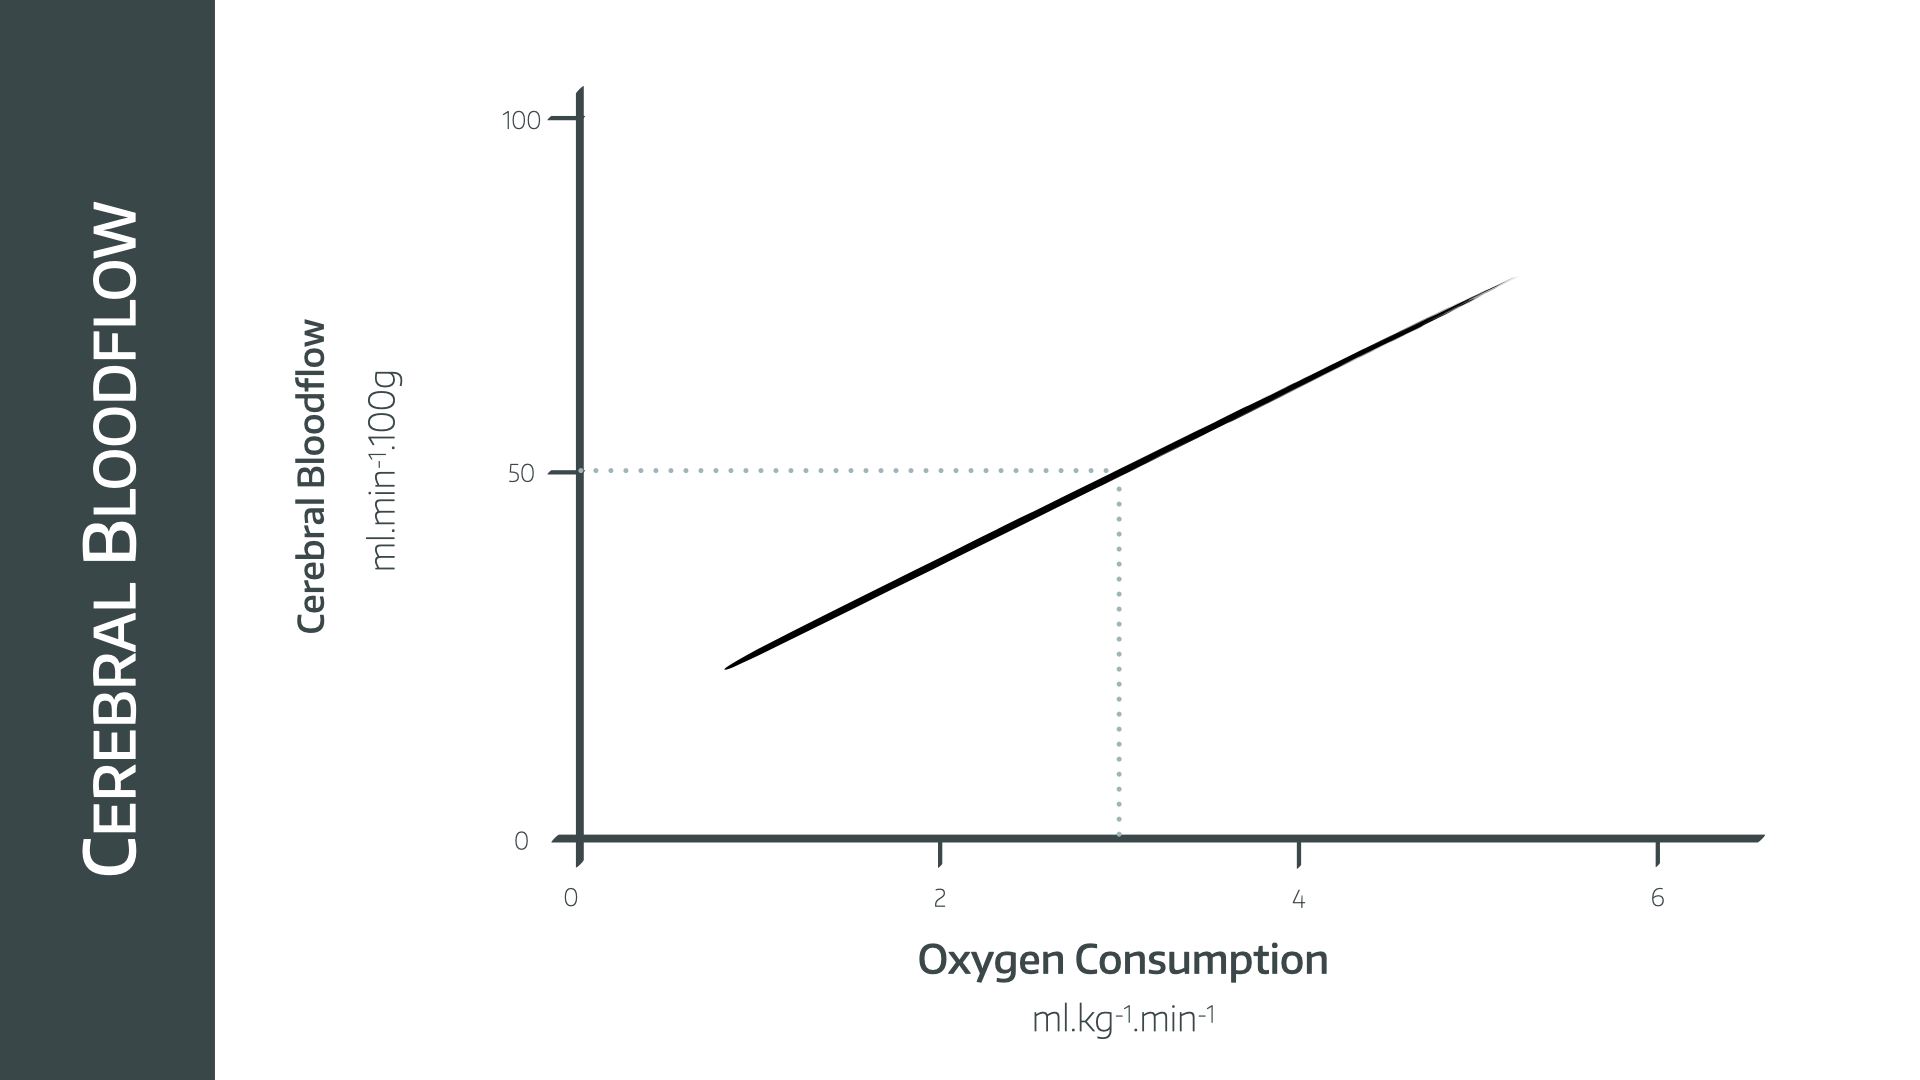
- There is a linear relationship between CBF and CMRO2
- Ischaemia occurs below 20ml/100g/minute
Can you draw and explain the intracranial pressure waveform?
If not, you will be able to in a minute.
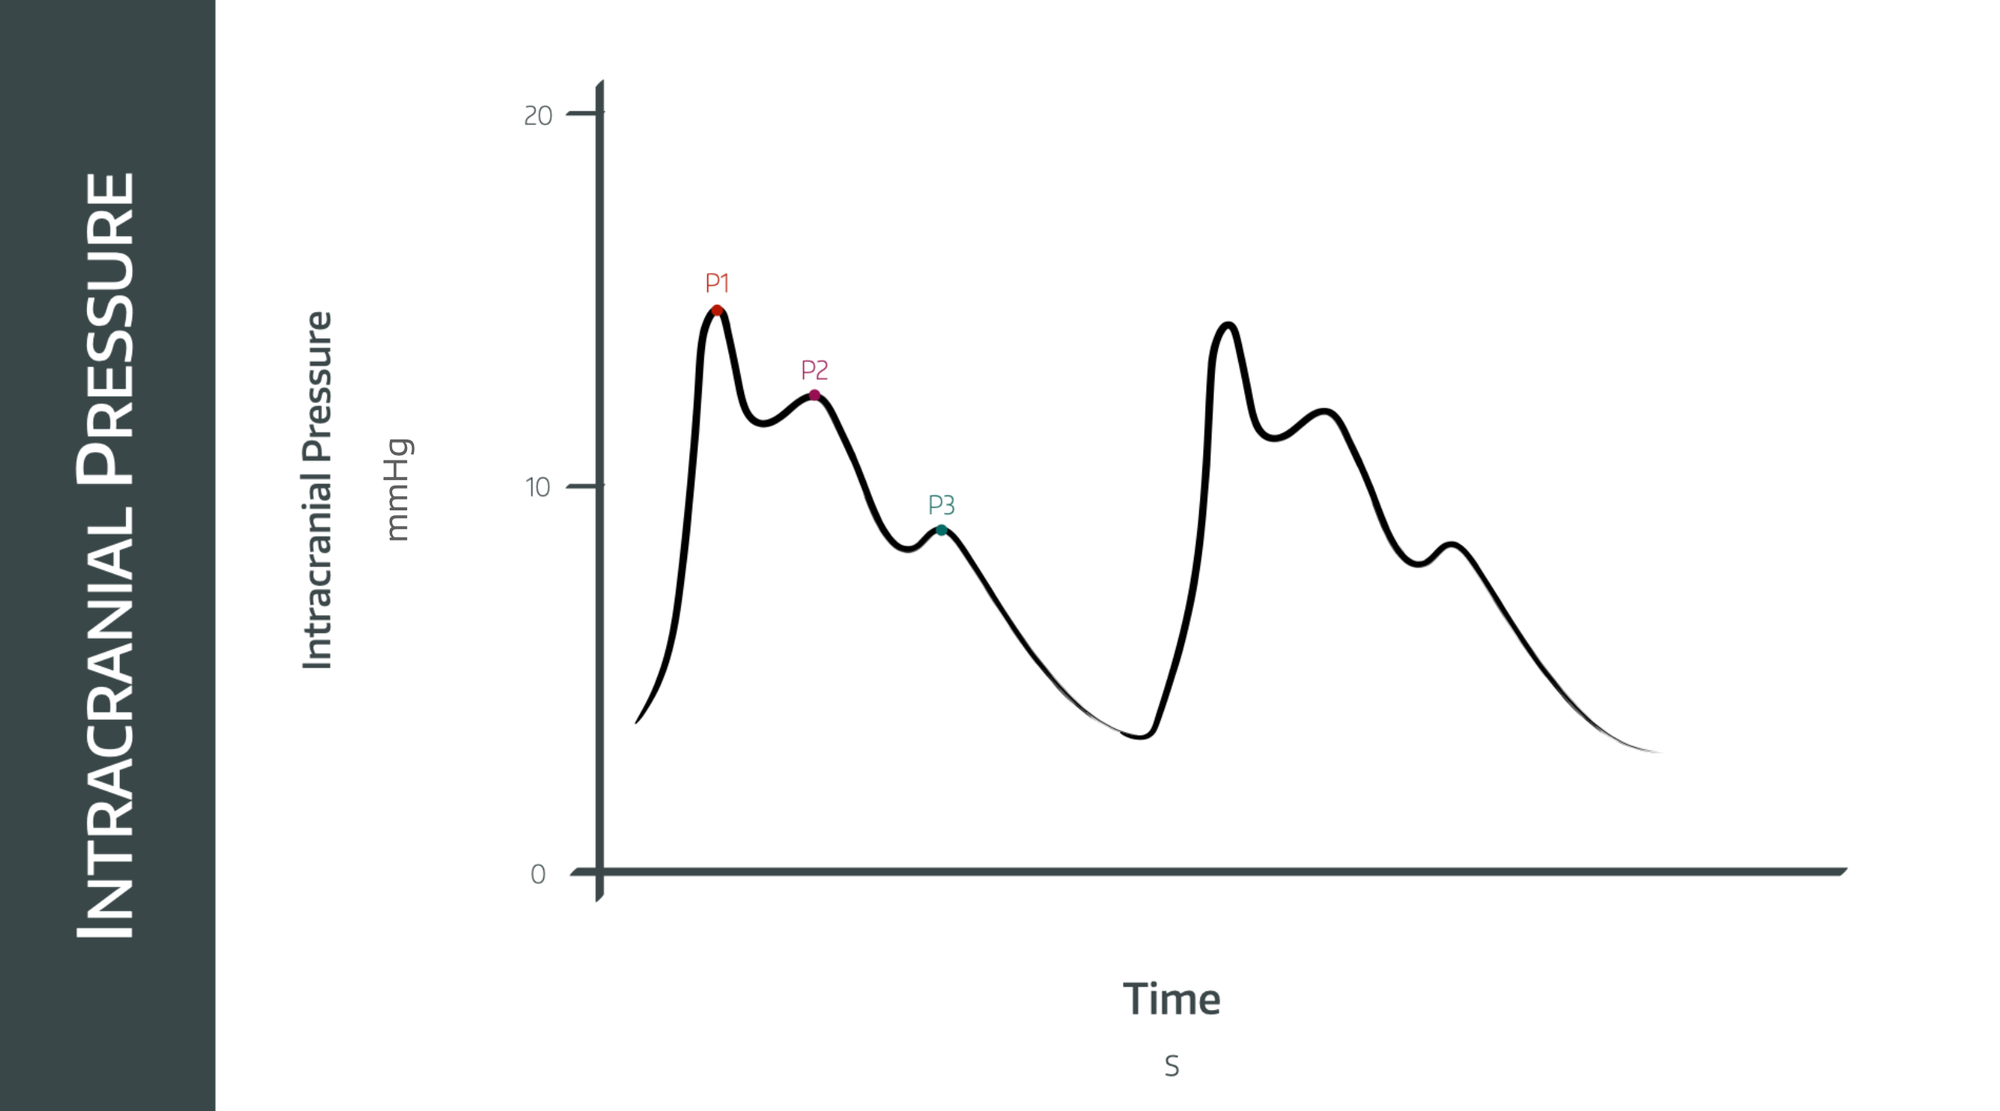
This essentially looks a lot like the invasive arterial pressure waveform, measured through an intracranial pressure transducer such as a ventricular drain or subarachnoid bolt.
The shape of the graph is vastly more important to know and explain than the specific numbers.
It has three pulse waves, each with gradually reducing amplitude.
The pulse waves
P1
- Percussive
- Transmitted arterial pressure
- Same as an arterial line trace
P2
- Tidal
- Due to arterial wave reflecting off brain tissue, so it varies with brain compliance
- Approximately 80% amplitude of P1
- Ends at point of dicrotic notch
P3
- Dicrotic wave
- Venous pressure wave, increases as CVP increases
As well as the three pulse waves in each beat, there are two other patterns in the overall pressure waveform:
Respiratory wave
This is a larger variation in baseline pressure with the respiratory cycle and is totally normal.
It's the same as the undulating 'swing' on your sats probe trace.
Slow waves
Also known as Lundberg waves, these are usually pathological, but not always.
Type A
- Plateau waves
- Rapid increase of baseline pressure to more than 50mmHg for between 2 and 20 minutes
- Demonstrate severely reduce compliance
- Always pathological
Type B
- 0.5 to 2 waves per minute
- Increases in pressure of around 20-30mmHg before returning to baseline
- Variable ICP usually present as well
- Sometimes due to vasospasm
Type C
- 4 to 8 waves per minute
- Up to 20mmHg
- May be normal
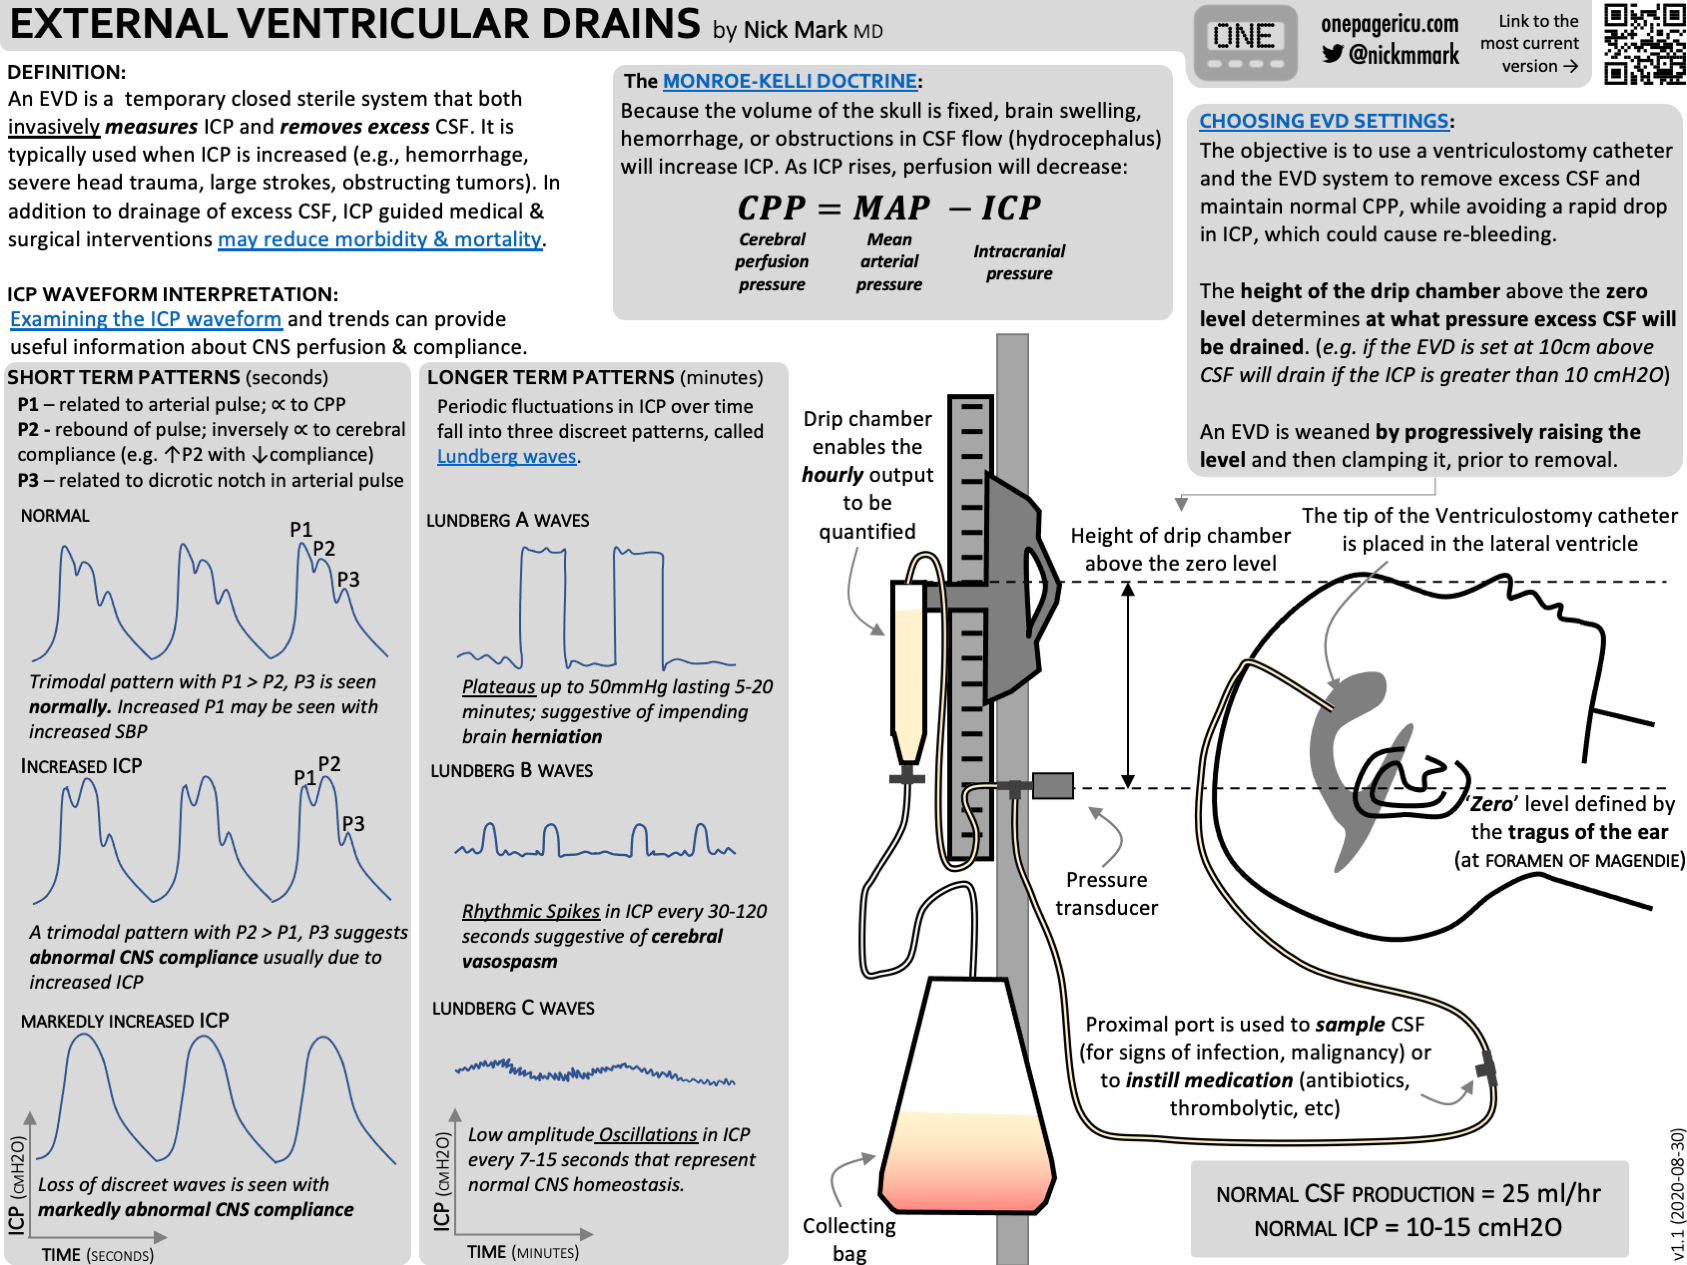
These images are beautifully represented in Dr Nick Mark's fabulous ICU one pager infographic, which you can find here, or in the resources section below.
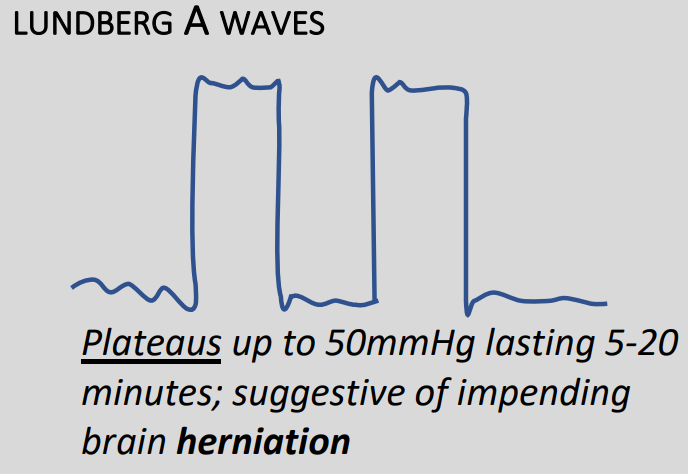
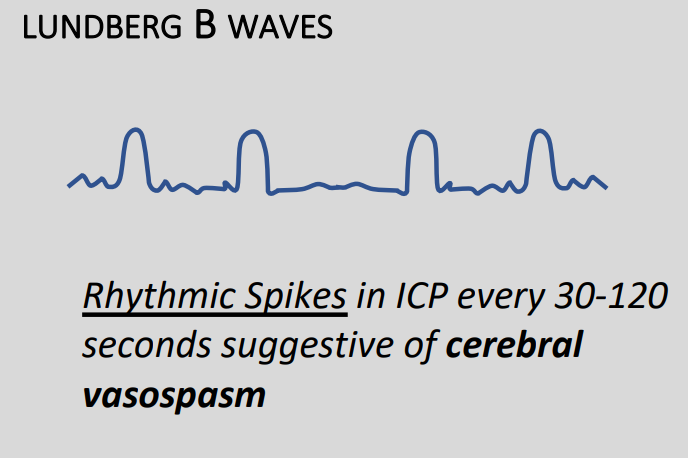
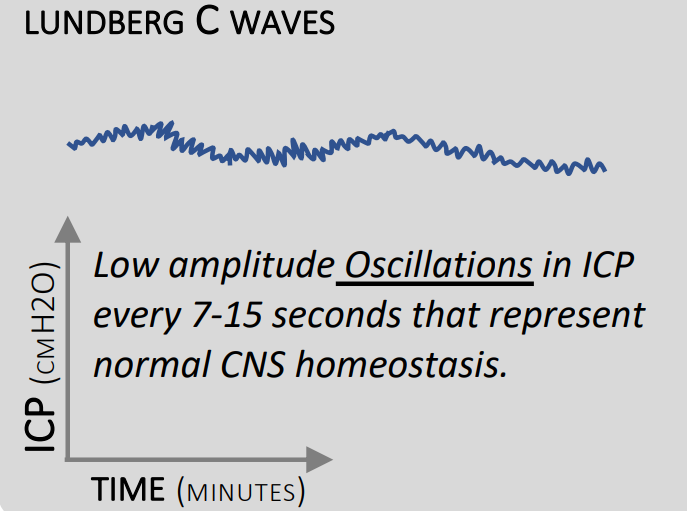
Shared with permission.
How does carbon dioxide affect intracranial pressure?
Hypercapnia causes vasodilatation and therefore increases cerebral blood flow as detailed above.
However above 11kPa, maximal vasodilatation is reached, and so there is minimal further increase in cerebral blood flow, and the graph levels out.
Low PaCO2 will cause vasoconstriction intially, however if this leads to ischaemia or hypoxia, these will trigger vasodilatation that will override the vasoconstriction.
Should we hyperventilate patients with high intracranial pressure?
Based on what we've just said, this seems like a logical plan on the face of it:
- Hyperventilate to reduce PaCO2
- Induce cerebral vasoconstriction
- Reduce intracranial pressure
However there is a problem with this:
- It's a temporary effect, and the brain rapidly recalibrates its set point for PaCO2 and will vasodilate again within a matter of a few hours
- Then when the hyperventilation stops, and the CO2 rises, the resulting rebound vasodilatation would be even worse than before
Therefore hyperventilation should only be done in absolute extremis as a temporising measure, for example in the ambulance when you're fifteen minutes away from definitive surgery and the patient starts showing signs of coning.
For all other scenarios, the focus should be on maintaining a low-normal PaCO2, and preventing avoidable vasodilatation.
Aim for a PaCO2 of 4-4.5kPa
This usually corresponds to an EtCO2 of 4.5-5.0 kPa (ish) but you should check a blood gas to check how the numbers line up for your patient.
Tell me about cerebral autoregulation
We're very nearly there I promise.
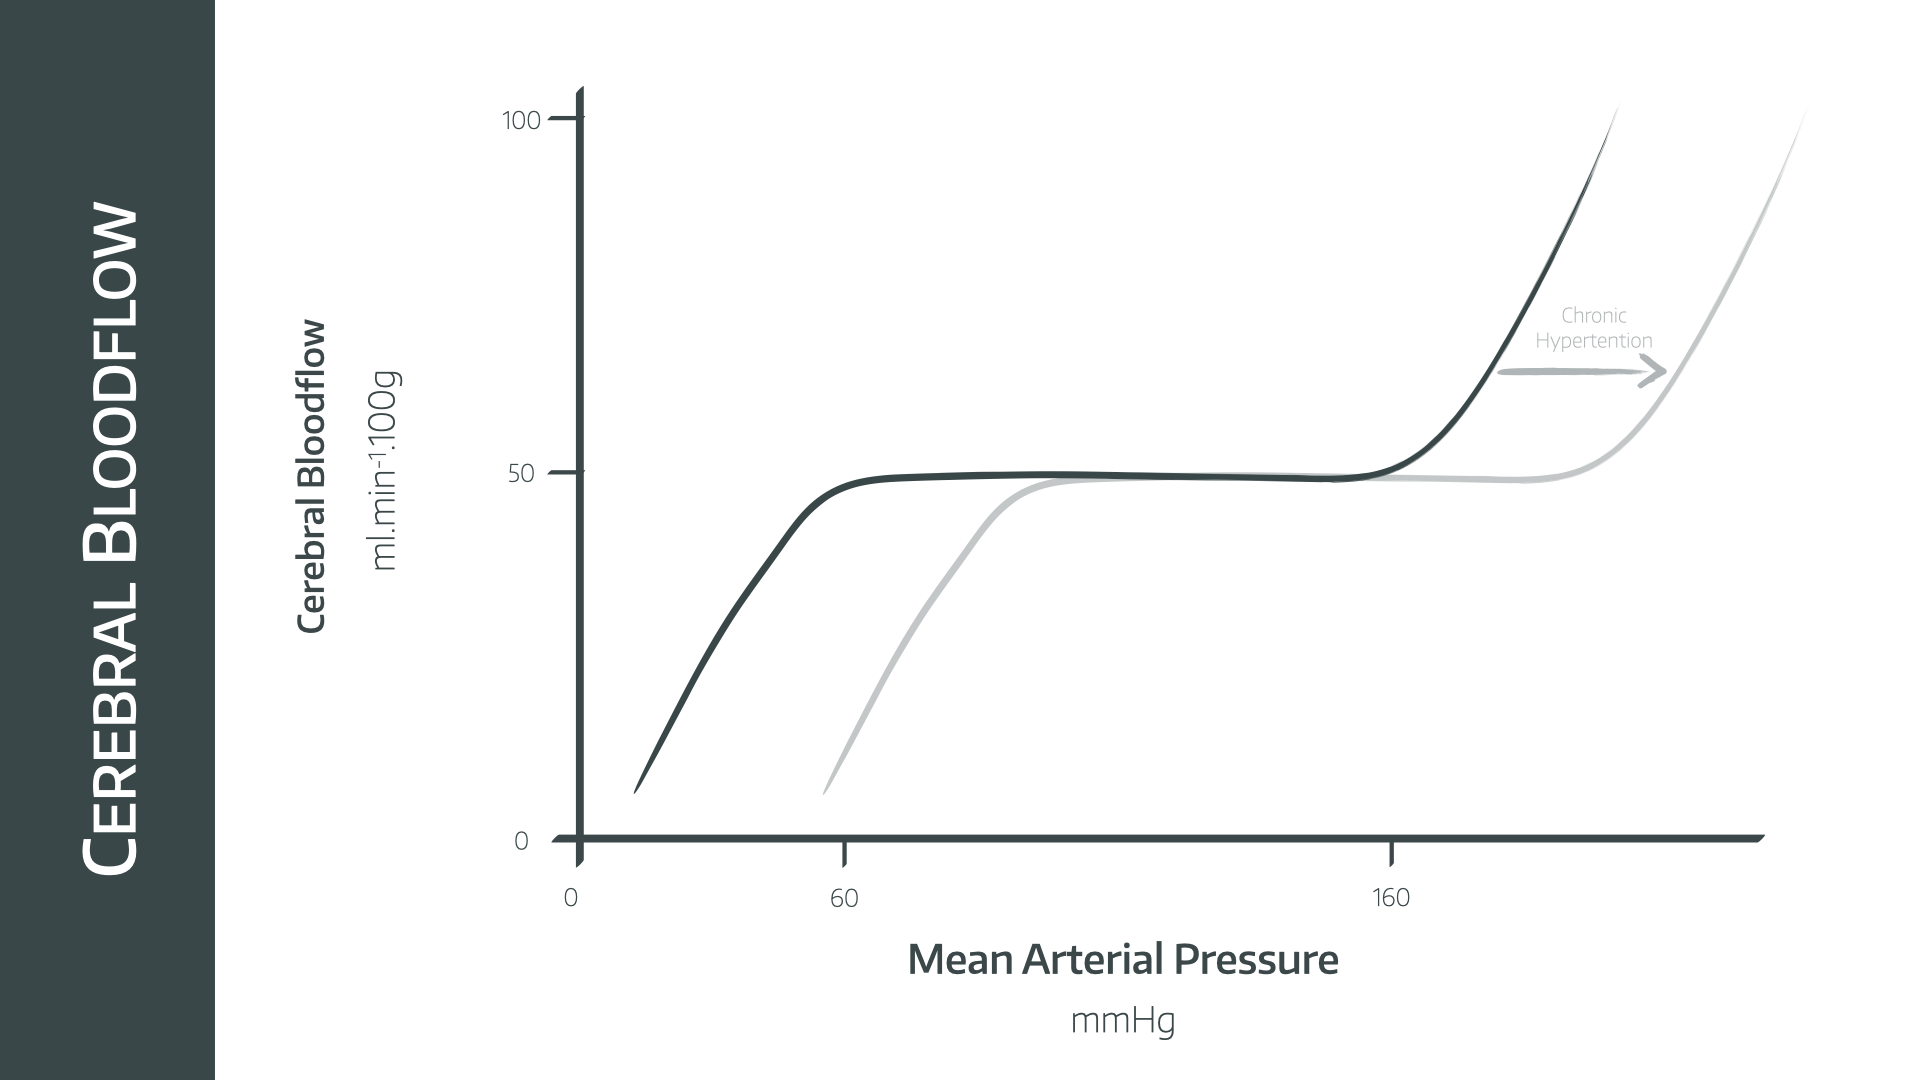
Autoregulation is the process by which an organ regulates its own blood flow, independent of perfusion pressure (within limits).
Both the brain and kidney demonstrate autoregulation.
Between 50 and 150mmHg of mean arterial pressure, the cerebral blood flow in a healthy brain remains steadfast at 50ml/100g/min.
This graph shifts to the right in chronic hypertension, emphasising the importance of maintaining sufficient MAP in known hypertensive patients under anaesthesia.
What effect does temperature have on CMRO2?
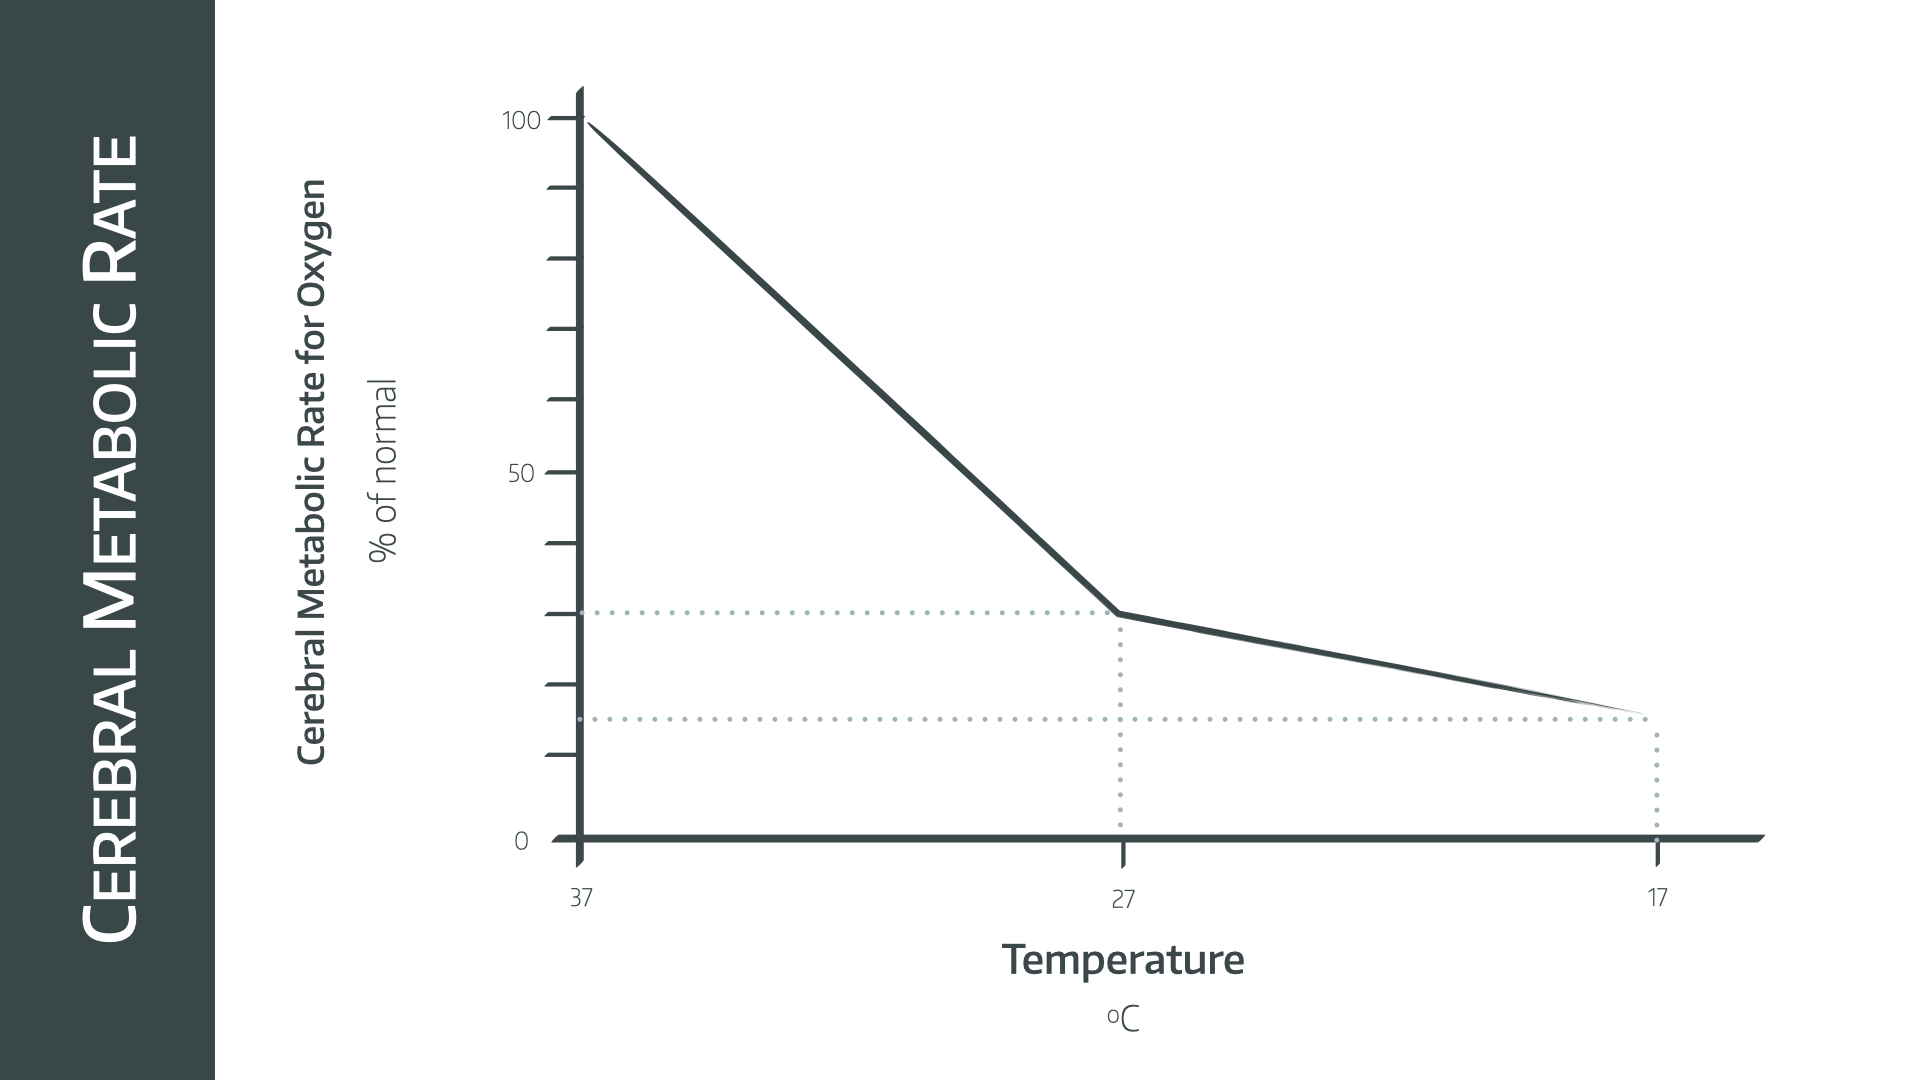
As temperature decreases CMRO2 decreases as well, which is part of the rationale behind targeted temperature management in out of hospital arrest patients and deep hypothermic cardiac bypass.
The graph has two linear segments, changing gradient at 27°C.
- 7% reduction for every 1°C temperature drop
- At 27°C it will be 30% of baseline metabolic rate
- At 17°C it will be 10% of baseline
And it seems to work, since we have insane journal articles like this one:

What effect do anaesthetic agents have on CMRO2?
The short answer is most of them reduce oxygen consumption as well as flow, but this isn't a universal rule.
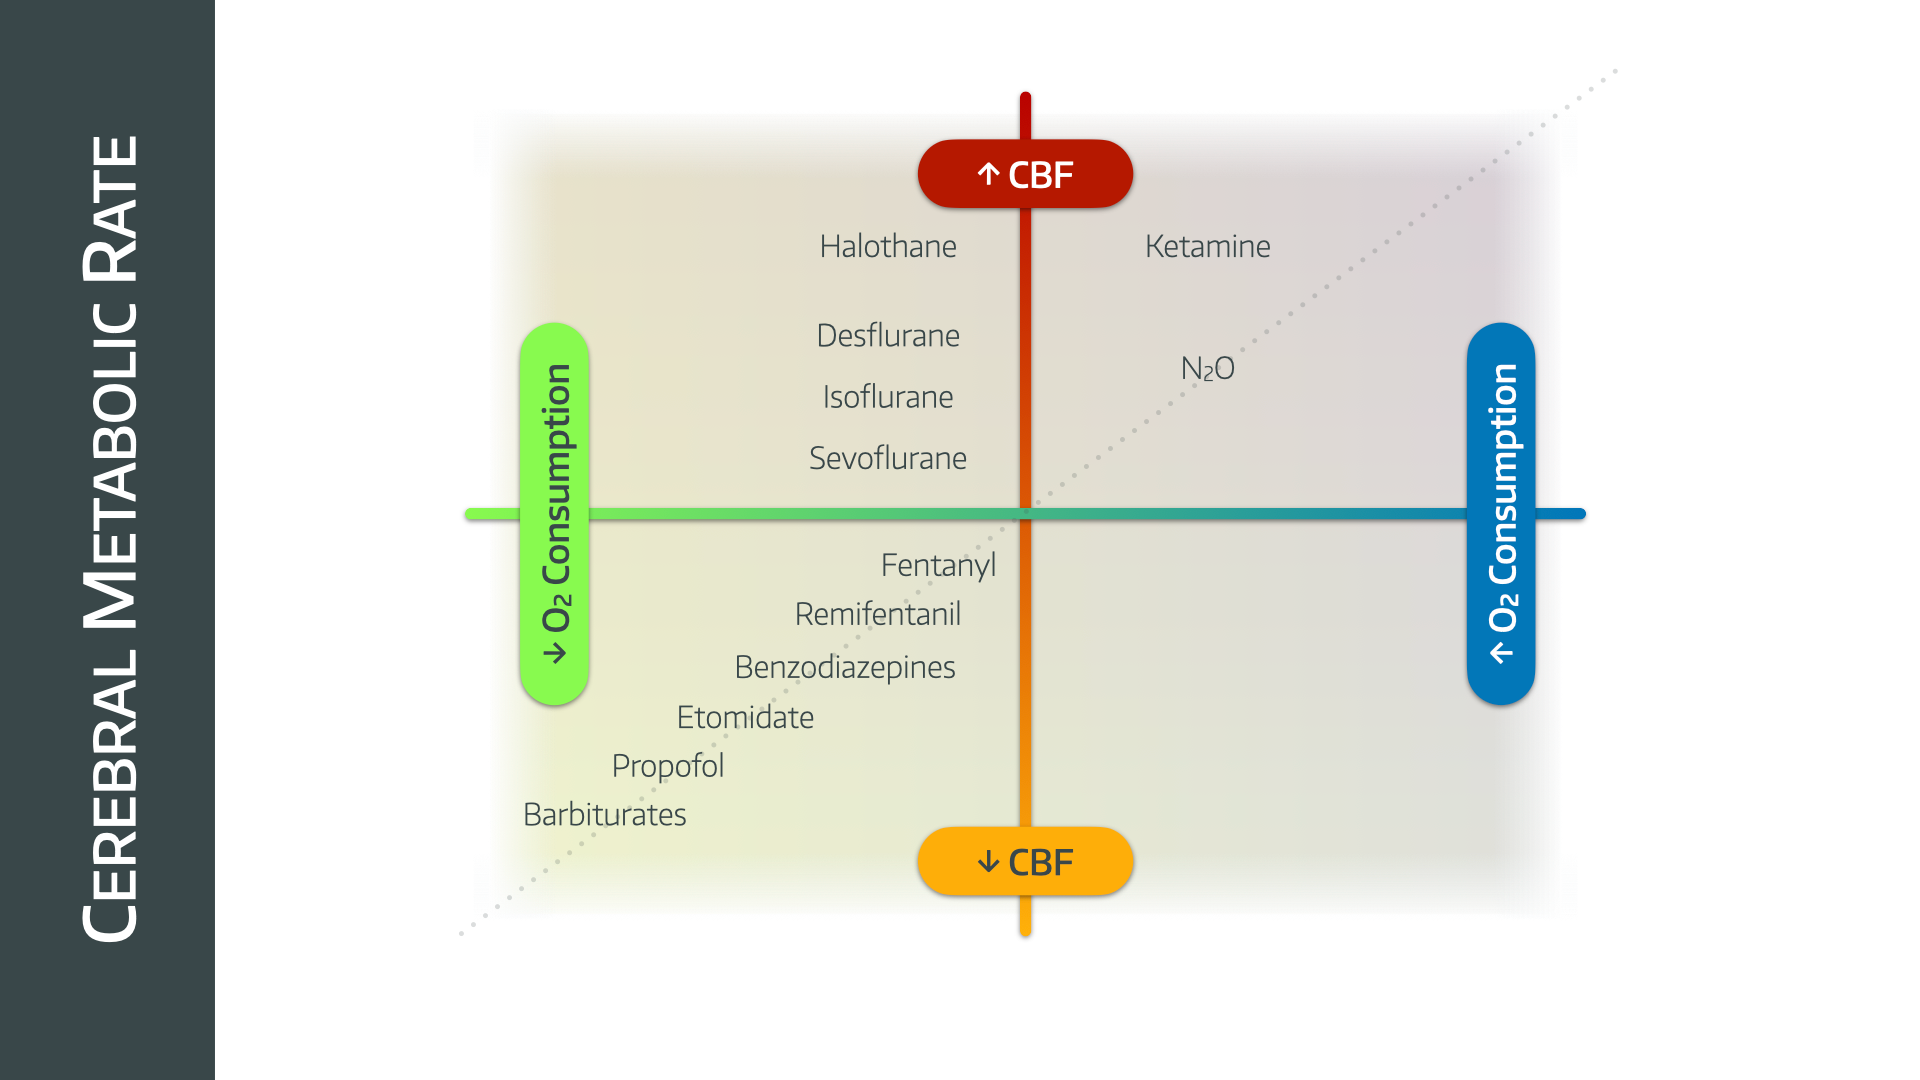
The dashed line is the graph depicting flow-metabolism coupling.
Inhalational agents
- Inhalational agents induce a dose-dependent vasodilatation apart from sevoflurane
- At 1.5 MAC cerebral autoregulation is disrupted
- Nitrous causes vasodilatation and also increases CMRO2
Intravenous agents
- Propofol and Thiopentone reduce CMRO2 and cerebral blood flow
- Ketamine increases CMRO2 and cerebral blood flow, but flow to a greater extent
- It is often avoided in patients with raised intracranial pressure for this reason, however it is frequently used for head trauma patients where cardiovascular stability is the overwhelming priority
What are the management options for raised intracranial pressure?
This is a common question at a variety of points during the FRCA exam journey, so it's worth investing some time to build a slick answer.
The categories we would suggest are pharmacological, non-pharmacological and surgical.
Pharmacological
- Fluids and vasopressors - to maintain perfusing pressure
- IV induction agents (except ketamine) - cause a dose dependent decrease in cerebral blood flow, pressure and metabolic rate
- Benzodiazepines - reduce blood flow and metabolic rate but not pressure
- Opiates - can decrease CMRO2 in large doses
- Muscle relaxants - useful to prevent coughing and straining
Just note that suxamethonium causes a transient increase in ICP, attenuated by induction agents such as thiopentone.
- Volatile agents - slight theoretical increase in ICP due to cerebral vasodilatation, but also reduce CMRO2 - Can be used at MAC <1
- N2O and Ketamine - Vasodilates and increases CMRO2, increasing ICP
- Barbiturates - deep thiopentone coma used in refractory seizures
- Phenytoin - used to prevent convulsions, it is a membrane stabiliser that prevents sodium and calcium influx during depolarisation
Mannitol
- Osmotic diuretic, filtered and not reabsorbed
- Withdraws water from brain across BBB
- Free radical scavenger and reduces CSF production
- 0.5 – 1ml/kg of 20% solution
Largely superseded by hypertonic saline.
Hypertonic saline
- 2-3ml/kg of 5% NaCl
- Hypertonicity draws fluid out of the interstitium into the blood to be drained away
Non-pharmacological
Main priorities
- Maintain oxygenation
- Prevent secondary brain injury
- Decrease ICP
- Optimise CPP
Ventilation
- PaCO2 4.0-4.5
- Hypocapnoea should be avoided to prevent vasoconstriction
Aid venous drainage
- Posture
- 30 degrees head up
- Head in midline
- No collars or tube ties
- PEEP minimal
Cooling is controversial
- Not shown to improve mortality however avoiding pyrexia does improve outcome
Surgical
Immediate neurosurgery is the only definitive treatment for raised intracranial pressure
- Debulking
- Drainage - via external ventricular drain
- Craniectomy
Apparently
If your patient has dilated ventricles causing catastrophic ICP, and you have no access to a neurosurgeon, you can put a needle through the orbit into the lateral ventricle and drain CSF that way...
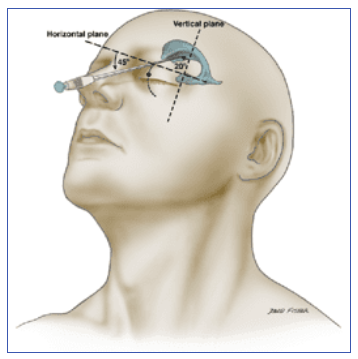
Please do not try this at home, in an ambulance, or at work in all honesty...
But you can read more about it here
 R. Tubbs

Okay we'll stop now.
Syllabus
- PB_BK_69 Intracranial pressure: cerebrospinal fluid, blood flow
Here's our post on head trauma
 Anaestheasier ltd.

 Anaestheasier ltd.

A Free Final CRQ
Our wonderful colleagues over at FRCA-revision have put together a whole series of high yield CRQ questions for the Final FRCA, and they also have a fantastic SBA and MCQ bank for the Primary. Tap the image below to go straight to the CRQ on intracranial pressure.

Useful Tweets and Resources
If you haven't already discovered Dr Nick Mark's amazing infographics over at ICU one pager - you simply must check them out
Cerebrospinal fluid shooting out in acute hydrocephalus with elevated intracranial pressure pic.twitter.com/hzqCbRmgQk
— Oren Gottfried, MD (@OGdukeneurosurg) April 19, 2023
From our #neuroanaesthesia series, our #cognitiveaid on effectively managing elevated intracranial pressure. #cognitiveaids #ascar #anaesthesia #anesthesia #icu #anesthesiology #icu #icunurse #ernurse #erdoc #icudoctor #foamed #medicalstudent #medicalschool pic.twitter.com/13JVuPPGwz
— ascargroup (@ascargroup) January 11, 2023
Looking for an audit idea?
Check out the RCOA's audit recipe book for neuroanaesthesia below.

References and Further Reading

 Alifia Tameem, MBBS MD FRCA

The Toolkits
Everything you need to smash the exams, all in one place.


Each toolkit purchase also wins you six months of free Anaestheasier membership.
Just a quick reminder that all information posted on Anaestheasier.com is for educational purposes only aimed at trained professionals, and it does not constitute medical or clinical advice.
Everything on this website is written by a trained (human) anaesthetist unless explicitly stated otherwise. LLMs may be used to assist with research and proofreading, but all writing is done by hand.
Anaestheasier should not be used as a definitive resource for academic writing; please reference original source material.
Anaestheasier® is a registered trademark.