Dear Novice

The following is a letter to myself as a novice anaesthetist at this point in the year with all the words I needed to hear - maybe someone else will find it helpful too.
If you know an anaesthetic trainee who might find these words helpful, please pass it along.
Dear Novice,
You're currently half way through your introductory training to anaesthesia and are well on your way to completion of IAC and joining the on-call rota.
By now you'll hopefully have given some anaesthetics, put some tubes between - or at least vaguely near - some vocal cords, and maybe stuck a needle in a few spines with varying success rates.
You might also have done some more independent inductions with the boss hovering outside, and maybe even been involved in an RSI or two.
You've also probably completely forgotten how to cannulate.
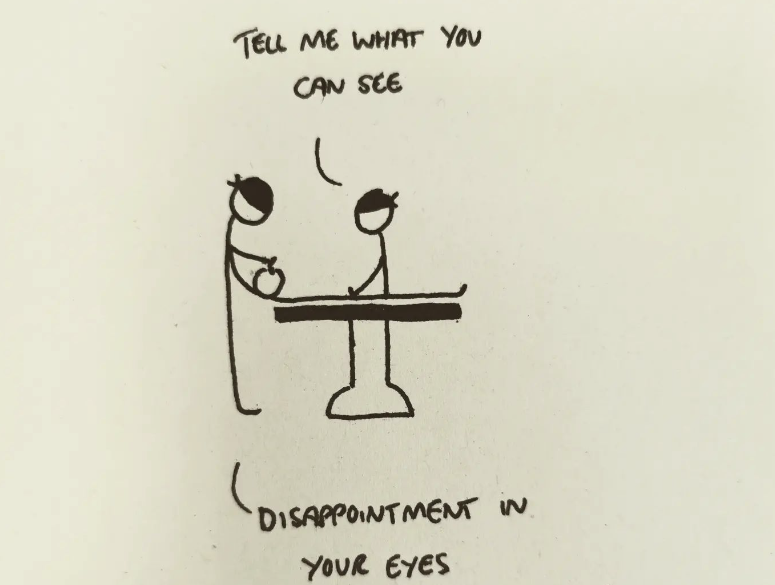
You're supposed to feel like this
If you're feeling something along the lines of
"How the hell am I supposed to do all of this on my own on call!?"
then please be reassured you are right on track.
You're meant to feel like that right now - that's the whole point of the novice period - to open your eyes to what you don't yet know.
If you were supposed to feel ready to go on call at this point, they would have made the novice period two months long.
It's three-to-four months for a reason, because it takes that much time to realise two things:
- Just how much you don't know yet
- How to use the knowledge you do have safely
If you find yourself feeling a little hesitant about the idea of doing anaesthesia by yourself at night time, it's a sign that you're paying enough attention to just how serious this job is, and the importance of your role.
Don't panic
It feels like a big deal going on call - and it is - but as professional neurotics we often inflate our own sense of responsibility and worry about things that probably don't need all that much concern.
"What if something comes up that I can't manage?"
I promise it's not a question of 'if', but 'when'.
Of course there's going to be a whole bunch of clinical scenarios that crop up that you've not seen or managed before. You know this because you've been seeing cases every day for the last few weeks that made you think 'I definitely wouldn't be happy doing this on my own'.
And that's the point.
Anaesthesia would be a very dull career indeed if everything could reasonably be managed by someone with three months' training, and one of the most rewarding parts of the job is getting more comfortable with thinking on your feet and improvising with what you have to hand, and using the variety of skills and techniques that you've accrued over your career.
But I realise that's not the priority right now.
Right now you'd probably just appreciate feeling comfortable giving a safe, sturdy anaesthetic that you feel confident is going to get the job done - and you will, in a few weeks' time.
That feeling where it just clicks, and you start to feel ready, is coming in due course.
There are very few cases that you will be expected to manage truly independently, and they will be the cases that you have probably been given free rein to induce and manage by yourself already, albeit with the consultant watching like a hawk from outside.
You're never alone
This is true in many senses.
Not only are you never doing something for a patient truly by yourself - you'll always have an ODP, anaesthetic nurse or ITU nurse helping you - but you also always have someone else you can call for help, whether that's the registrar, consultant or a friendly ITU doctor.
I vividly remember the first time I gave an anaesthetic independently out of hours.
It went something like this
"Okay - roc's in," I announced, to no-one in particular, purely out of nervous habit as the plunger sank the muscle relaxant silently into the patient's arm, the beeping monitor gently reminding me that the patient and I were equally stressed about our encounter.
I shakily twisted the barrel of the syringe back off the cannula (that I was thrilled to have actually managed to insert all by myself) and set it back down on the anaesthetic machine.
Taking hold of the mask with unpleasantly sweaty gloved hands, I watched the clock for those breathtaking (literally) forty-five seconds while the paralytic permeated through every nook and cranny of the thirty-two year old mother-of-three that I'd met half an hour ago.
Then it hit me like a brick - It's three a.m. and I've just rendered a stranger unconscious and unable to breathe, and now I have to keep them alive by myself.
The following thoughts then arrived neatly in order:
- What if I can't intubate her?
- What if she arrests?
- Who let me have this job?
- How did I even get a medical degree?
My express train to panic-ville was interrupted by the decidedly underwhelmed ODP who gently handed me the laryngoscope and held the patient's mouth open, taking care to clear the lower lip from the bottom teeth as I slid the laryngoscope over the tongue.
"You're going to be fine, take your time" she soothed, in a voice that suggested I very much was not her first novice-on-the-rota-for-the-first-time intubation.
"I can see the cords!"
"You sound surprised..."
"I am."
Fifteen seconds later I had an alive, asleep and intubated patient in front of me, and I was grinning like a moron.
"Maybe some sevo?" she hinted in the manner of a very bored OSCE examiner whose candidate has clearly forgotten the whole point of the station.
"Ah shit thanks."
Use your ODP
Most of the ODPs and anaesthetic nurses can manage an airway just fine all by themselves, and could talk you through a sensible anaesthetic plan without batting an eyelid, so use them.
They are your co-pilot, and they will keep you and the patient safe if you let them.
I regularly ask my ODP and anaesthetic nurse colleagues for ideas and suggestions about how best to anaesthetise a patient, what airway usually works well for this procedure, or whether they think I've missed anything, especially if it's 3am and I'm overthinking things more than I need to.
So in the middle of the night, if you're feeling the weight of the world on your shoulders, remember that everyone in the room is on your team and will be able to help you out far more than you realise.
Trust your gut
There will be times when you're asked to do something that makes you feel very uncomfortable.
Examples from my own experience include:
- Please can you sedate this 2 year old child in Majors so we can relocate her elbow?
- Please can you sedate this 96 year old woman with atrial fibrillation for a cardioversion? Her systolic is 63.
- Please can you put a central line in on the ward so that we can give TPN?
- Please can you do a quick GA for this guy with severe aortic stenosis, lung fibrosis and renal failure? It'll be a super quick laparotomy
- This man has a NELA mortality risk score of 56%, can you assess whether he's fit for an operation?
- Is this ECG okay?
- Can we do it under local with, like - just a little bit of muscle relaxant?
We're the handy-people of the hospital, called upon for the weird and wonderful odd jobs, bits and bobs that other specialties need help with, and often the other specialties are rather 'optimistic' about what we're able to achieve with a syringe of hypnotic and some plastic tubes.
It's what anaesthetists do, no matter how senior. I have seen very experienced consultants ask a colleague to simply be in the room with them for higher risk cases or particularly young children, if only for moral support as much as genuine assistance.
There is no bravado, no cope culture, no 'just get it done' mentality that plagues many of our fellow medical teams in the hospital.
If you're not happy - call for help.
There will be many, many times when you call for help in the middle of the night and end up not needing it, and the senior you called in from their bed will just be delighted that everything went okay.
Never be rushed
Anaesthetists are graceful creatures, gliding swiftly and smoothly through the turbulence of resus and the chaos of labour ward, gently fixing and quietly correcting as we go before disappearing into the ether.
Or sevoflurane, take your pick.
We do not rush.
At this point I'll refer you to Anaestheasier's ninth rule of anaesthesia - your lack of planning does not constitute my emergency.
It is easier said than done, but there is never a situation in which you need to rush, because rushing ends up being clumsy and disjointed and much slower than just being methodical, calm and smooth.
Other people will try to rush you, to get you to fix their emergency right now because of course it's the most important emergency in the whole hospital and their patient is the only patient that matters right now.
- You will have theatre coordinators telling you to go and see patients right now
- You will have ED docs requesting analgesia reviews right now
- You will have surgeons demanding you just get on with it and hurry up
- You will have cardiologists proclaiming that they need to revascularise and the patient should already be intubated by now
- You will have ward doctors saying this patient needs their cannula for their vancomycin that was due seven hours ago right now
And that's fine.
Don't get drawn into their haste.
Of course there are situations where you may need to act quickly and intervene, but you never need to become hurried.
Just breathe, assess, plan, and do your thing. I promise you can take your time, because in reality even if you feel like you're moving slowly, it'll be more than fast enough.
The art of Swanning
Swanning is the essential skill of appearing serenely calm and unwavering in your control of the situation, even if you're frantically paddling away underwater just to stay afloat.
One of the key roles of the anaesthetist in any situation is to be the sturdy anchor of reassurance for both your team and your patient, even if you're thoroughly bricking it behind the drapes.
If the anaesthetist panics, everyone panics.
Swanning is not a personality trait; rather it is a trainable skill that will come with time and practice, just so long as you pay attention and plan ahead.
I am an anxious wreck
I always have been.
I am very open about this, because I feel that a lot of other people are as well but don't feel they can talk about it in a career that prides itself on never showing weakness.
I am and always have been terrified of making mistakes, and as a foundation doctor I would regularly wake up in sweats at three in the morning in a blind panic over something as devastatingly serious as whether I'd prescribed the correct rate of fluids or missed a mildly raised CRP for a patient who's already on antibiotics.
I never thought I could be an anaesthetist.
I couldn't imagine handling the pressure.
One of my biggest fears, especially as a novice anaesthetist, was that I'm not a 'chilled enough' person to do anaesthetics, or to be effective in a crisis. Everyone else seemed much more relaxed than I was, more in control and totally unfazed by the concept that we literally nearly kill people for a job.
Don't get me wrong - swanning is most certainly not acting like you don't need help or pretending you know what to do when you don't - far from it. Instead it's the ability to enact what you do know in a controlled and methodical way, and ensuring you have back up available when you need it.
It took time to realise that in truth, everyone is swanning and giving off the appearance of being completely unflustered while hiding a heart rate of 130bpm - you just need to practice.
So if everyone else around you seems dead calm while you're stressed out then please be reassured that this is entirely normal, and as you become more confident managing airways, accidents and asystoles, you too will evolve into the chilled out steady hand on the tiller that the team looks to in a crisis.
Talk to us
I hope that at least part of this post has provided a morsel of reassurance or entertainment, and that your training in anaesthetics is as enjoyable as it is challenging.
We're two anaesthetic registrars that love teaching, mentoring and generally helping other trainees out, so please don't hesitate to get in touch if you have any questions or concerns - we'd be delighted to hear from you - and I guarantee that if you ask a question, someone else will be glad you asked it for them!
- Anaestheasier@gmail.com if you'd rather remain anonymous
- Or comment below
And as always, if you have read something that doesn't make sense, that you disagree with or that is plain wrong then please do let us know - we love feedback and discussion about ideas. Equally if you have your own advice for your fellow colleagues then please share in the comments or via email.
Otherwise - happy gassing!
Other useful stuff
 Anaestheasier ltd.

 Anaestheasier ltd.



 unicyclemedic

I may have also written this
Just a quick reminder that all information posted on Anaestheasier.com is for educational purposes only aimed at trained professionals, and it does not constitute medical or clinical advice.
Everything on this website is written by a trained (human) anaesthetist unless explicitly stated otherwise. LLMs may be used to assist with research and brainstorming, but all writing is done by hand.
Anaestheasier should not be used as a definitive resource for academic writing, please reference original source material.
Anaestheasier® is a registered trademark.